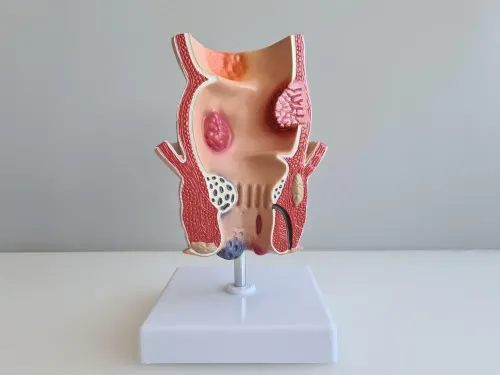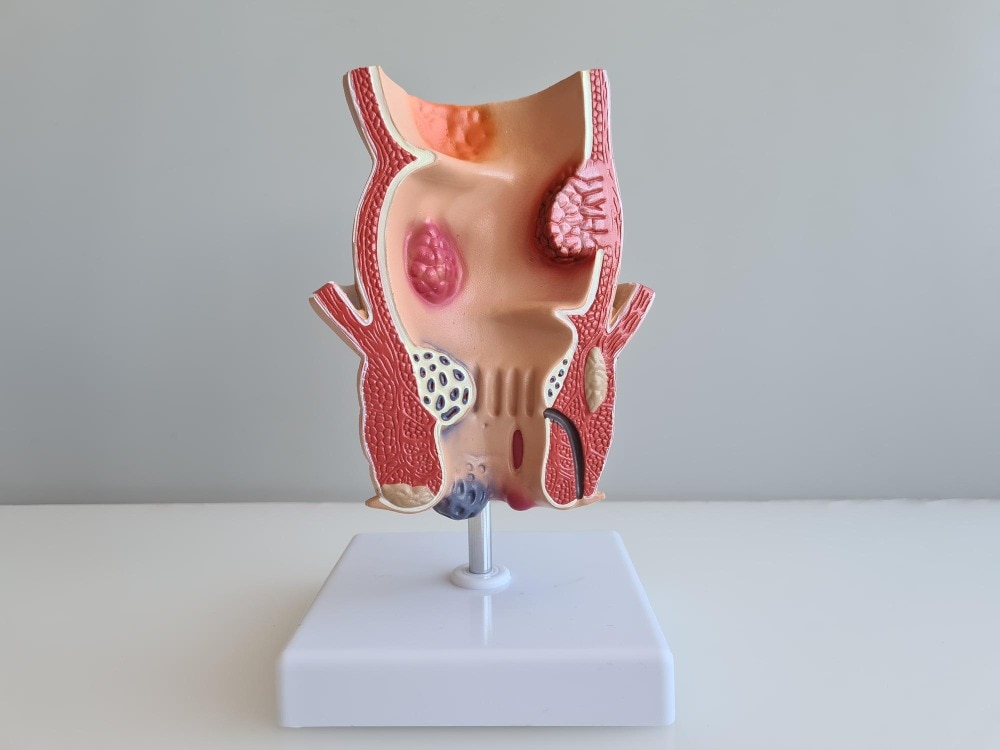
Rectal bleeding, anal pain, itching, or a lump does not prove that you have piles, and the urgency depends on the symptom pattern. You will be able to decide when to seek emergency care, when to arrange an examination, which treatments to compare, and what to check before choosing a hospital in Pune.
Key takeaways
- Get unexplained or recurrent bleeding examined before assuming it is piles.
- Compare medicines, office procedures, and surgery by symptoms and recovery time.
- Ask about diagnosis, anaesthesia, technique, risks, costs, and follow-up.
- Arrange transport and home help before procedures requiring sedation or surgery.
Match your symptoms to the right level of care
Painless bleeding is not proof of piles. Recurrent or unexplained bleeding needs examination before you search for a piles surgery hospital in Pune for symptoms; anal fissure, fistula, abscess, colorectal polyps, inflammatory bowel disease, and colorectal cancer can look similar.
1. Seek emergency assessment for heavy or ongoing bleeding, black stools, dizziness or fainting, fever with pus, rapidly worsening pain, inability to pass urine, or a prolapsed lump that cannot be pushed back. Do not wait for a routine appointment.
2. Arrange a prompt surgical review for recurrent bleeding, a painful or bluish anal swelling, or a lump that repeatedly prolapses but can still be pushed back. A suddenly painful bluish lump may be a thrombosed external haemorrhoid, whose treatment timing depends on severity and how early you present.
3. Book a routine consultation for persistent itching, occasional painless bleeding, or a reducible lump without severe pain. Constipation, straining, skin irritation, and other conditions still need assessment if symptoms persist.
A clinician will take your history, inspect the anal area, and perform a digital rectal examination. Anoscopy or proctoscopy may show internal haemorrhoids; colonoscopy is considered when the bleeding pattern, your age, screening status, bowel changes, anaemia, or other findings suggest a colonic cause. Do not self-diagnose from an online symptom list.
Compare non-surgical care, office procedures, and surgery
Mild symptoms, an unconfirmed diagnosis, untreated constipation, or improvement with basic care favour non-operative treatment. Increase fibre, drink adequate fluids, avoid straining, and limit toilet sitting; a stool softener can help short term. Use topical steroid or anaesthetic creams only briefly: prolonged use can thin skin, mask worsening disease, or irritate the area.
Do not take laxatives unsupervised.
Office procedures treat selected internal haemorrhoids without the recovery burden of an operation. Rubber-band ligation suits many grade I–II and selected grade III haemorrhoids; sclerotherapy and infrared coagulation suit smaller bleeding haemorrhoids. They can recur and are not appropriate for every prolapse or external lump.
| Treatment | Invasiveness and recurrence | When it fits |
|---|---|---|
| Rubber-band ligation, sclerotherapy, infrared coagulation | Low invasiveness; recurrence remains possible | Selected internal haemorrhoids |
| Haemorrhoidectomy | More painful recovery; more definitive for advanced disease | Grade III–IV prolapse, combined internal/external disease, persistent symptoms |
| Stapled haemorrhoidopexy | Less early pain, but higher recurrence and specific risks | Selected prolapse; not automatically superior |
| Haemorrhoidal artery ligation | Less early pain, but recurrence rises with advanced prolapse | Selected internal disease after discussing trade-offs |
Recurrent prolapse, a lump that cannot be pushed back, repeated bleeding despite treatment, thrombosed external piles, combined disease, or persistent severe pain support surgical assessment. Surgery is a poor first choice for constipation that has not been treated or symptoms that settle with conservative care. Compare these options before booking piles treatment in Pune.
Know what happens at the consultation and what to ask
Keep a seven-day record before the appointment: bleeding amount and frequency, pain, swelling or prolapse, itching, bowel frequency, stool hardness, straining, and whether a lump returns inside. Bring current reports and a medicine list.
- Mark anticoagulants such as warfarin, apixaban, rivaroxaban, dabigatran, or aspirin.
- Record diabetes, its treatment, and recent glucose results.
- Note previous anorectal procedures, operations, and complications.
- Do not stop a blood thinner unless the prescribing doctor gives instructions.
A proper consultation includes symptom history, bowel-habit review, inspection of the anal area, digital rectal examination, and medication review. The surgeon may perform anoscopy when internal haemorrhoids need direct assessment; colonoscopy is considered when bleeding, age, screening status, or other findings suggest a colonic cause.
| Ask | What a useful answer identifies | Warning sign |
|---|---|---|
| What is the confirmed diagnosis and grade of internal haemorrhoids? | Whether piles explain the symptoms | An operation offered before examination |
| Why this procedure, and what are the alternatives? | Trade-offs against medicines or office treatment | “Advanced” or “best” without evidence |
| What anaesthesia, pain, recurrence risk, and complications apply? | Recovery and procedure-specific risks | No named risks |
| How many visits, is removed tissue sent for pathology, and whom do I call urgently? | Total practical burden and emergency access | No contact route |
Surgery deserves scrutiny when constipation is untreated or symptoms improve with conservative care. Ask the surgeon to explain why the proposed operation is justified for your findings, not merely for a marketing label.
Plan recovery, transport, and help after each procedure
Office treatments usually allow same-day travel, but surgery needs a recovery plan. After rubber-band ligation, sclerotherapy, or infrared coagulation, expect pressure, soreness, or light bleeding. After haemorrhoidectomy, stapled haemorrhoidopexy, or haemorrhoidal artery ligation, arrange a responsible adult, especially after anaesthesia or if pain limits movement.
| Procedure | Recovery plan |
|---|---|
| Rubber-band ligation | Fibre, fluids, and soft stools; light bleeding can occur as the banded tissue falls. Return to desk work when comfortable; avoid driving while taking opioid pain medicine. |
| Sclerotherapy or infrared coagulation | Mild soreness or bleeding; keep bowel movements soft and resume activity gradually. Follow the clinic’s review plan. |
| Haemorrhoidectomy | Expect significant pain and an open wound; use prescribed analgesia, warm sitz baths, gentle washing, and stool softener. Delay driving, heavy work, and strenuous exercise until movement is comfortable. |
| Stapled haemorrhoidopexy | Recovery is often easier than excisional surgery, but urgency, bleeding, or recurrence still requires review. Follow wound, medicine, and activity instructions. |
| Haemorrhoidal artery ligation | Early pain may be lower, but prolapse or recurrence can occur; follow-up confirms the result. |
Do not strain or sit on the toilet for long. Contact the treating hospital urgently for fever, pus, worsening pain, heavy bleeding, dizziness, urinary difficulty, or a prolapse that cannot be pushed back.
A suddenly painful bluish external lump may be thrombosed; early severe cases can need excision, while later cases may need analgesia and stool regulation.
Plan follow-up visits in Pune and choose a hospital you can reach, not piles surgery in pune based only on reputation. Recovery claims mean little unless they name the procedure.
Use a hospital checklist, not a marketing label
Choose the hospital by its anorectal checklist, not by a “best” or “advanced” label. A general surgeon is suitable for a confirmed, straightforward haemorrhoid case; colorectal expertise is useful for recurrent prolapse, advanced disease, previous failed treatment, or uncertain diagnosis.
Ask whether the facility provides:
- An appropriately credentialled general or colorectal surgeon
- Examination, anoscopy or proctoscopy, and colorectal diagnostic access
- Anaesthesia, recovery monitoring, and pain-control support
- 24-hour emergency evaluation or a named urgent-care route
- Pathology review when tissue is removed
- Documented infection-control procedures
- Written informed consent covering alternatives, risks, and recurrence
- A specific follow-up schedule and contact number
Persistent unexplained bleeding may need gastroenterology, colonoscopy, or another colorectal pathway instead of immediate surgery. Verify NABH accreditation for the specific facility and its accredited scope; do not infer it from an advertisement. NABH accreditation addresses defined standards such as patient care, infection control, patient rights, and facility management.
Dr Masal Hospital 08042755436 is one Pune option to contact with questions about who examines you, surgical availability, anaesthesia, emergency arrangements, pathology, and follow-up.
Compare surgical treatment in Pune across the factors that affect your actual burden:
| Factor | What to verify | Why it matters |
|---|---|---|
| Diagnosis | Confirmed haemorrhoids and grade | Prevents wrong-site or unnecessary treatment |
| Surgeon fit | General or colorectal experience with the proposed procedure | Matches complexity to skill |
| Safety and access | Anaesthesia, infection control, emergency cover, travel time | Limits avoidable risk and delays |
| Total burden | Visits, recovery help, transport, complication plan | Shows the real cost beyond the operation fee |
Frequently asked questions
When should you seek medical care for suspected piles symptoms?
Seek examination for recurrent or unexplained bleeding, because fissures, fistulas, abscesses, polyps, inflammatory bowel disease, and colorectal cancer can look similar to piles.
How do non-surgical care, office procedures, and piles surgery differ?
Non-surgical care uses measures such as fibre, fluids, stool-softening treatment, and symptom relief. Office procedures treat selected haemorrhoids without major surgery, while surgery is considered when symptoms, prolapse, or failed earlier treatment justify it.
What should you ask during a piles consultation?
Ask how the diagnosis was confirmed, which treatment fits your symptoms, whether anaesthesia is needed, what risks and costs apply, how long recovery takes, and when follow-up will occur.
How should you plan recovery after piles treatment?
Confirm whether you need an escort, transport, time away from work, prescription medicines, dietary changes, wound care, and help at home during the first recovery period.
How can you compare hospitals for piles treatment in Pune?
Use a checklist covering surgeon credentials, examination and diagnosis, anaesthesia support, emergency arrangements, written estimates, infection-control practices, follow-up access, and clear answers about recovery.