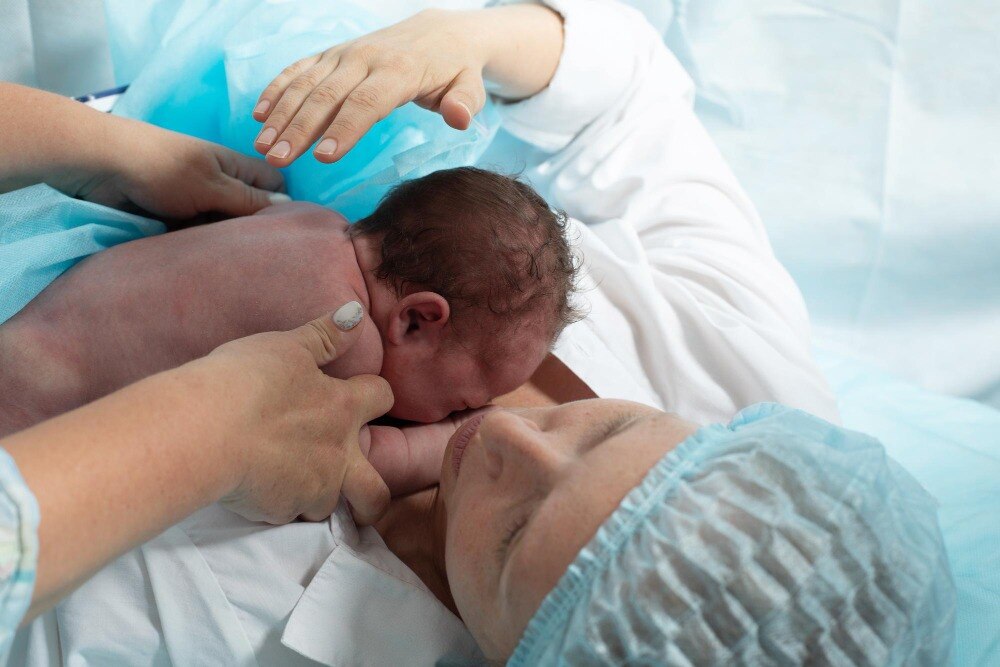
The right delivery plan depends on your health, the baby’s position and condition, the placenta, previous uterine surgery and how labor progresses—not on a universal ranking of vaginal birth over cesarean birth. By comparing the routes, their timelines, risks, preparation and recovery, you can ask more precise questions about the safest plan for this pregnancy.
Key takeaways
- A planned C-section differs from an emergency C-section triggered by danger during labor.
- Ask your obstetrician when to call for bleeding, reduced fetal movement, or severe pain.
- Plan for longer movement restrictions and wound care after a C-section.
- Discuss future pregnancy risks before choosing a delivery route when both options are safe.
What happens during vaginal birth and C-section?
Spontaneous vaginal birth begins when contractions and cervical changes start on their own, followed by pushing and birth through the vagina. The other routes change either how labor starts or how the baby is delivered.
| Option | How it starts | How birth happens |
|---|---|---|
| Spontaneous vaginal birth | Labor begins naturally with contractions, cervical dilation, and effacement. | You push after full dilation; the baby passes through the vagina. |
| Induced labor | Medication, a balloon catheter, or breaking the waters starts or strengthens labor. | After cervical dilation and pushing, birth proceeds vaginally if labor progresses safely. |
| Assisted vaginal birth | Labor reaches full dilation, but pushing is ineffective, prolonged, or the baby needs help to be born. | A vacuum cup or forceps guides the baby out; a cesarean is used if assisted birth is unsuitable. |
| Planned C-section | The operation is scheduled before labor, based on findings such as placenta previa or certain uterine scars. | Spinal or epidural anesthesia numbs the lower body while the surgeon opens the abdomen and uterus to remove the baby. |
| Emergency C-section | Fetal distress, heavy bleeding, cord problems, or stalled labor creates an urgent concern during pregnancy or labor. | The team moves quickly to cesarean birth after assessing the mother, baby, and urgency. |
An attempted vaginal birth can change to an emergency C-section when the fetal heart pattern remains concerning, the cervix stops progressing despite treatment, or vaginal birth is no longer safe. A prior cesarean does not automatically rule out labor; eligibility depends on the uterine incision, pregnancy details, and immediate surgical capability.
When is a planned C-section recommended, and when does labor become an emergency?
A planned cesarean is justified when vaginal birth poses a higher risk than surgery. Common indications include placenta previa covering the cervix, a transverse lie that cannot be corrected, a previous classical uterine incision, selected major uterine surgery, some multiple pregnancies, or a condition requiring early birth.
Breech presentation needs individual assessment: external cephalic version, planned vaginal breech birth with an experienced team, or cesarean may be discussed. Without another indication, elective cesarean is usually scheduled at 39 weeks or later.
| Situation | Finding | Usual decision |
|---|---|---|
| Placenta or fetal position | Placenta covers the cervix, or the baby remains transverse | Plan cesarean |
| Previous uterine surgery | Classical incision or surgery that weakens the uterine wall | Plan cesarean |
| Labor complication | Cervix stops dilating or the baby fails to descend despite adequate contractions | Cesarean if corrective steps fail |
| Fetal or maternal emergency | Persistent nonreassuring heart-rate pattern, cord prolapse, major bleeding, placental abruption, or suspected uterine rupture | Emergency cesarean when birth cannot be safely delayed |
During attempted vaginal birth, clinicians first assess the fetal heart rate, cervical change, descent, contractions, bleeding, pain, and maternal vital signs. They may stop oxytocin, change position, give fluids, treat low blood pressure, or use vacuum or forceps when appropriate.
If the danger persists, or labor remains arrested after adequate time and contractions, they recommend emergency cesarean.
With Dr Vinayak Masal, verify his current obstetric role and credentials directly, and ask how your gestational age, fetal presentation, placenta location, prior uterine surgery, TOLAC suitability, anesthesia plan, and emergency backup affect the recommendation.
What preparation and hospital timeline should you expect?
At admission, the team checks your vital signs, pregnancy records, fetal heart rate and labor pattern. They assess the cervix by examination: labor progresses toward 10 cm dilation, and pushing begins only after full dilation and descent of the baby.
| Route | Preparation and birth | Immediate timeline |
|---|---|---|
| Vaginal birth | You usually have blood tests, consent for possible procedures, and an intravenous line for fluids or medicines. Follow fasting instructions; do not eat if an epidural, anesthesia, or urgent surgery could become necessary. An epidural is optional when available. A bladder catheter is used briefly if an epidural makes urination difficult. | Pushing can last minutes or longer, depending on parity, fetal position and progress. After birth, staff monitor bleeding, blood pressure, pain, urination and the baby’s breathing and temperature for several hours. |
| Planned or emergency C-section | You sign surgical consent, have blood tests and an intravenous line, and fast according to hospital instructions; urgent surgery proceeds without waiting for a complete fasting period. A urinary catheter is placed after anesthesia. Spinal or combined spinal-epidural anesthesia is usual; general anesthesia is used when regional anesthesia is unsuitable or immediate birth is critical. Cervical dilation and pushing are not required. | The operation commonly takes about 45–60 minutes, although an emergency procedure may begin within minutes. You then spend time in a recovery area while staff monitor bleeding, blood pressure, anesthesia effects, pain and the baby. |
For a planned C-section, ask when to stop solid food and clear liquids. Bring medication details and disclose allergies, prior anesthesia problems and previous uterine surgery.
How do the benefits and risks compare for mother, baby and future pregnancies?
Vaginal birth usually avoids abdominal surgery and supports faster recovery, but it can involve perineal tears, pelvic-floor symptoms, assisted birth, heavy bleeding or an emergency C-section. A planned C-section avoids labor-related tearing but adds surgical risks and a longer recovery.
| Option | Practical benefits | Important complications |
|---|---|---|
| Vaginal birth | No abdominal incision; usually earlier mobility and shorter recovery; lower surgical infection and blood-clot risk | Perineal tear, pelvic-floor weakness or incontinence, postpartum hemorrhage, assisted birth, failed labor or emergency C-section; the baby can develop breathing difficulty after a difficult or assisted birth |
| C-section | Predictable timing when medically indicated; avoids labor, severe tearing and some birth injuries | Incision infection, hemorrhage or transfusion, blood clots, anesthesia or organ injury, longer recovery; planned cesarean birth also increases newborn breathing problems, especially before 39 weeks |
Failed labor can lead to an emergency operation after exhaustion, infection risk and bleeding have increased. After a previous C-section, trial of labor after cesarean (TOLAC) can be appropriate, but uterine rupture is a rare emergency; risk depends on the uterine-incision type, prior surgery, number of cesareans and hospital access to immediate surgery.
A cesarean also raises risks in later pregnancies, including placenta previa, placenta accreta spectrum, adhesions and surgical injury. Accreta risk rises with each cesarean, particularly when placenta previa is present. Ask Dr Vinayak Masal to review your indication, placenta location, prior uterine surgery, TOLAC suitability and emergency plan.
How does recovery differ after vaginal birth and C-section?
An uncomplicated vaginal birth usually allows earlier walking and a quicker return to routine activity, but perineal soreness can make sitting, urination and bowel movements painful. A C-section causes abdominal incision pain, restricted movement and a longer recovery because it is major surgery.
| Option | Early pain and movement | Care, lifting and breastfeeding |
|---|---|---|
| Vaginal birth | Perineal soreness or stitches; walk as soon as advised | Rinse and pat the area dry; lift only what feels comfortable; side-lying or upright feeding can reduce pressure |
| C-section | Incision pain when standing, coughing or getting out of bed; walking is gradual | Keep the incision clean and dry; hold the baby but avoid heavier lifting until cleared; side-lying or football-hold feeding protects the abdomen |
Do not drive until you can brake, turn and check traffic without pain, are not taking sedating medicines, and your clinician and insurer permit it. Return to exercise, sex, work and heavier household tasks only when bleeding, pain, wound healing and energy levels support them.
Take specific questions to consultation. At Dr Masal Hospital 08042755436, ask whether Dr Vinayak Masal currently provides obstetric care and request his current qualifications.
- What is the indication, gestational age, fetal presentation and placenta location?
- How do prior uterine surgery or a previous C-section affect vaginal birth?
- What anesthesia, emergency plan and recovery restrictions apply?
- When can you drive, lift, exercise and return to work?
- How could this birth affect a future pregnancy?
Related service
Consultation ₹500 Best Gynecology & Obstetrics Hospital for Comprehensive Women’s Care At Masal Hospital, women receive complete, compassionate, and advanced care... View service → |
Frequently asked questions
What happens during vaginal birth and a C-section?
Vaginal birth involves contractions, cervical dilation, pushing, and delivery through the vagina. A C-section delivers the baby through surgical cuts in the abdomen and uterus, usually under regional anesthesia.
When is a planned C-section recommended?
A planned C-section can be recommended for conditions such as placenta previa, certain fetal positions, some previous uterine surgeries, or when vaginal birth presents a clear medical risk.
When does labor become an emergency?
Labor becomes an emergency when the mother or baby shows signs of immediate danger, such as heavy bleeding, severe fetal heart-rate abnormalities, cord prolapse, or suspected uterine rupture.
How does recovery differ after vaginal birth and C-section?
Vaginal recovery is often faster, though tears and pelvic soreness can require care. C-section recovery includes incision care, pain control, and restrictions on lifting and strenuous activity while the abdominal wound heals.
Keywords